How the Anion Gap Helps in Salicylate Poisoning
The anion gap is a useful clue in the workup of salicylate poisoning, but it should in no case be treated as a single diagnosis. In toxicology, the gap helps identify hidden acids in the blood and guides the broader acid-base balance assessment. Because aspirin exposure can produce more than one disturbance at the same time, the anion gap is often part of a more extensive laboratory interpretation rather than a single decisive number.
Classic aspirin toxicity often creates a mixed acid-base disorder. At first, salicylates stimulate the respiratory center, leading to respiratory alkalosis through compensatory hyperventilation. As the poisoning advances, organic acids and impaired metabolism contribute to metabolic acidosis. The result is a pattern that can seem puzzling if you focus only on one value. The anion gap becomes a diagnostic clue that helps link the serum chemistry findings to the underlying toxicology evaluation.
Salicylates interfere with cellular metabolism and can disrupt oxidative phosphorylation, which promotes the accumulation of organic acids. These metabolic derangements lower buffering capacity and may increase the anion gap. At the same time, patients may present with tachypnea, nausea, vomiting, altered mental status, or other signs of systemic toxicity. In this setting, the anion gap supports clinical correlation rather than replacing it.
A normal or only mildly elevated anion gap does not exclude salicylate poisoning, especially when the acid-base pattern is evolving.
How to Use an Anion Gap Calculator
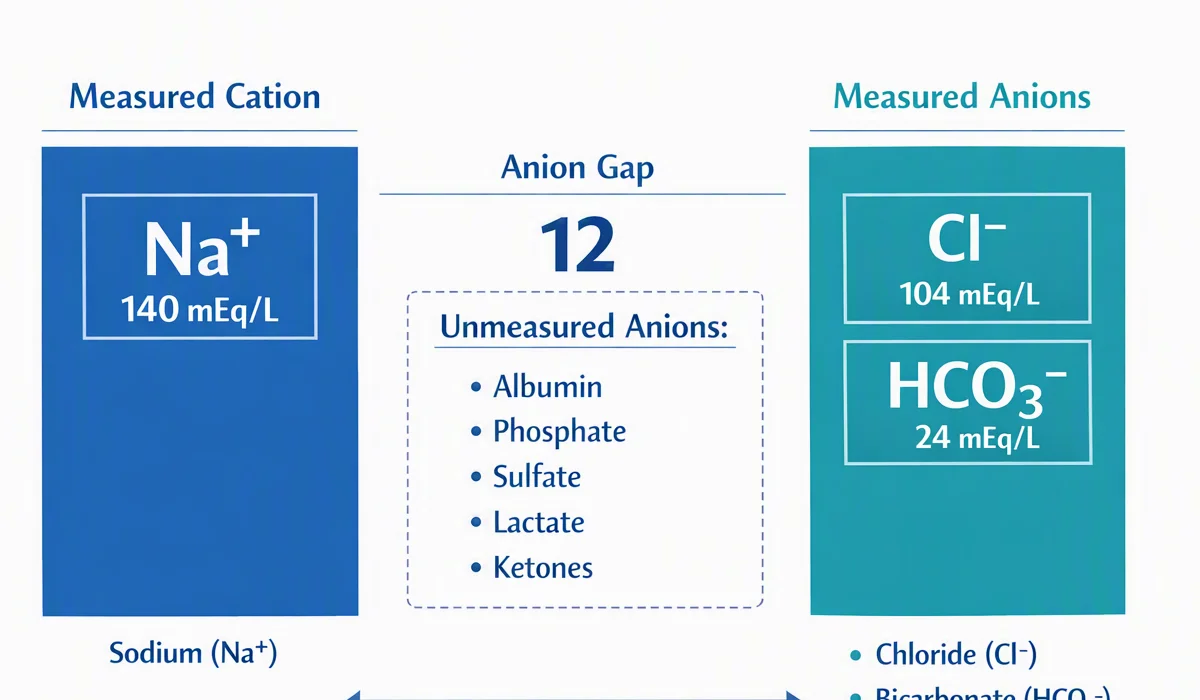
An anion gap calculator is a useful tool for rapid laboratory interpretation during emergency assessment and poisoning workup. The usual calculation usually uses serum sodium, serum chloride, and serum bicarbonate. In its typical form, the formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Using the calculator begins with reliable serum chemistry values. Initially, enter the sodium concentration. Next, add the chloride and bicarbonate concentrations. Subtract that sum from sodium to obtain the gap. This simple anion gap calculation can quickly identify whether there is an unusual accumulation of unmeasured anions.
In suspected salicylate poisoning, the calculator should be used as part of a broader diagnostic workflow. Look at the numerical value, but also consider the patient's symptoms, respiratory rate, mental status, and other evidence of electrolyte abnormalities. A raised number may support systemic toxicity, while a borderline result may still be clinically important if the complete picture suggests aspirin exposure.
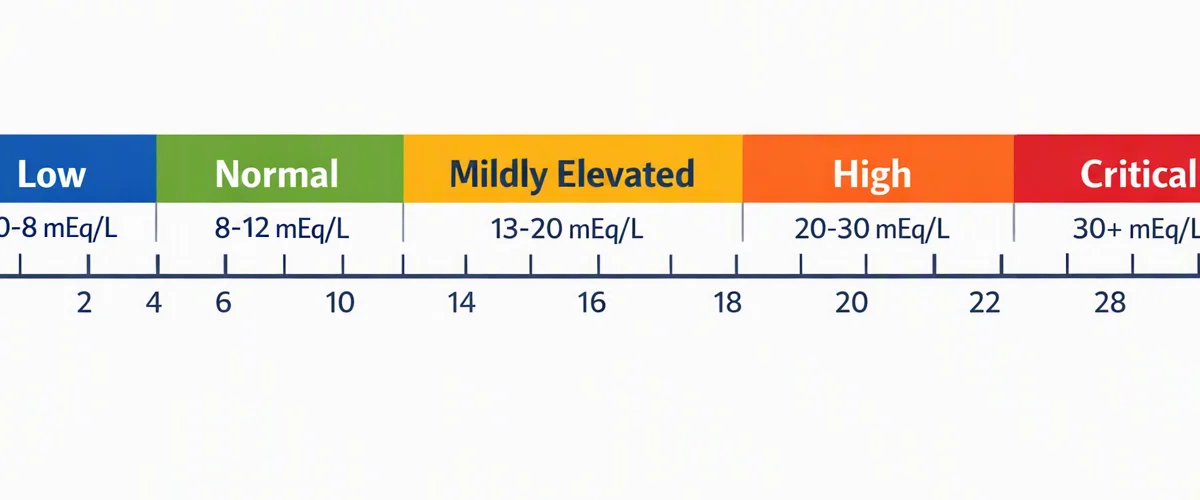
It is also important to compare the calculated result with the laboratory’s reference range if one is provided. Different institutions may use slightly different methods or reference values, which affects laboratory interpretation. The goal is not simply to identify an abnormal number, but to use that number to guide toxicology evaluation and further testing.
Classic Laboratory Patterns in Aspirin Toxicity
Aspirin toxicity often shows its mixed and occasionally shifting lab profile. A common early pattern is respiratory alkalosis with a low or falling bicarbonate, followed by metabolic acidosis as salicylate burden builds. This is why an arterial blood gas is often helpful. The arterial blood gas provides direct information about pH, carbon dioxide, and bicarbonate status, helping confirm the presence of a combined acid-base disturbance.
Patients with salicylate poisoning may show a reduced carbon dioxide level because of hyperventilation. At the same time, the bicarbonate may be decreased due to the metabolic component. The anion gap may increase as acids accumulate. This creates a diagnostic challenge: a patient can have almost normal pH if respiratory alkalosis and metabolic acidosis counteract one another. That is one reason clinicians should not depend on pH alone when evaluating a potential toxic ingestion.
Lactate may also be raised in aspirin toxicity. However, elevated lactate does not by itself explain the disturbance by itself. Salicylates can hinder energy production and drive acid generation beyond simple tissue hypoperfusion. Therefore, lactate is a helpful part of the poisoning workup, but it should be interpreted in conjunction with the anion gap, arterial blood gas, and the rest of the clinical data.
Another key pattern is that https://anion-gap-calculation.com/physiology/electroneutrality.html the severity of symptoms does not necessarily match the first available lab values. Early testing may overlook the full metabolic derangement. Repeat assessment is often required because the toxicology evaluation can evolve quickly. A patient may progress from a relatively subtle pattern to severe systemic toxicity over a short time.
Corrected Anion Gap and albumin correction
Albumin is the chief unmeasured anion in the blood, so decreased albumin can make the anion gap look deceptively unchanged. This is particularly relevant in hypoalbuminemia, where the standard gap may miss the true burden of unmeasured acids. For that reason, a corrected anion gap is often more accurate when acid-base interpretation is important clinically.
In suspected salicylate poisoning, albumin adjustment helps keep from missing a hidden high-gap state. If albumin is reduced, the measured anion gap should be corrected before concluding that the serum chemistry is normal. This step improves diagnostic accuracy and lowers the chance of false reassurance in a patient with possible toxic ingestion.
Corrected values are especially useful when other findings point toward poisoning despite a slightly abnormal number. For example, a patient may have tachypnea, nausea, ringing in the ears, and an arterial blood gas suggesting mixed acid-base disorder, yet the initial gap is only mildly elevated. In that setting, albumin correction can uncover a more meaningful abnormality and improve acid-base interpretation.
Albumin adjustment is not only about mathematics. It is about matching the laboratory pattern to the patient's physiologic state. In clinical practice, the corrected anion gap helps synthesize acid-base balance, serum chemistry, and toxicology evaluation so the clinician can identify systemic toxicity earlier.
When a High Anion Gap Causes Concern
A increased anion gap in the right clinical context should signal a serious underlying condition. In salicylate poisoning, this may indicate accumulated organic acids and impaired metabolism. However, the differential diagnosis is extensive, and the gap should prompt a systematic evaluation rather than an assumption of a cause.
Other common explanations include ketone production from diabetes, fasting, or alcohol-related situations, and renal failure, where acid clearance is impaired. A toxic ingestion can also produce a high gap, including salicylates, methanol, ethylene glycol, or other agents. This is why the anion gap calculator is best viewed as a screening and triage tool within a larger diagnostic workflow.
When the gap is raised, ask whether the pattern fits the story. Does the patient have respiratory alkalosis and metabolic acidosis together? Are there symptoms that suggest aspirin exposure? Is there evidence of dehydration, reduced kidney function, or glucose abnormalities that might indicate another explanation? These questions support clinical correlation and prevent misinterpretation.
The anion gap also matters because a rising value can signal increasing metabolic derangement. Even if the patient initially appears unchanged, an increasing gap along with increasing symptoms may indicate advancing systemic toxicity. In that setting, repeat testing and rapid toxicology evaluation become even more important.
Clinical Subsequent Actions Once You Calculate the Gap
After calculating the gap, the next move is to connect the result to the overall poisoning workup. If salicylate poisoning is suspected, obtain a salicylate level as soon as possible. This is important because the anion gap alone cannot quantify exposure or severity. A level helps support the diagnosis, follow trends, and guide treatment decisions.
Review the full set of electrolytes, including sodium, chloride, bicarbonate, potassium, and any other available serum chemistry markers. Electrolyte abnormalities are often seen in toxic states and can affect acid-base balance. If the patient is clinically concerning, a repeat blood gas and repeat chemistry panel may be needed to follow the course.
Repeat testing is particularly useful when the presentation is early or unclear. Salicylate concentrations may rise after the initial sample if absorption continues, especially with enteric-coated products or delayed gastric emptying. The acid-base disorder may also evolve, shifting from mixed respiratory alkalosis and metabolic acidosis toward more severe acidemia.
Reach out to poison control early when aspirin toxicity is possible. Expert guidance can help interpret the laboratory pattern, recommend follow-up testing, and support management decisions. Poison control is especially useful when the case interpretation is complicated by coexisting disease, uncertain timing, or ambiguous lab results.
At this stage, the key is synthesis. The anion gap calculator provides one data point, but toxicology evaluation depends on the whole picture: symptoms, lab trends, salicylate level, arterial blood gas findings, and the clinical course.
Shortcomings of the Anion Gap in Salicylate Poisoning
This anion gap has practical value, but it also has major limitations. A typical anion gap does never eliminate salicylate poisoning, especially in the early stage of poisoning or in patients with hypoalbuminemia or mixed disorders that obscure the expected finding. This remains one of the most critical reasons not to rely on the calculator alone.
Incorrect reassurance can happen when doctors anticipate a significant gap increase and miss concerning signs. During the initial phase, alkalosis from breathing too much may dominate, and the metabolic component may not yet be clearly apparent. A patient can therefore seem sick while the gap remains normal or near normal. That is why the result must be interpreted with clinical reasoning rather than treated as a test to exclude it.
Another limitation is that acid-base analysis can be affected by concurrent illness. Kidney failure may disturb the baseline chemistry. Ketone buildup can on its own increase the gap. Additional metabolic abnormalities can mask the classic pattern of aspirin toxicity. In these situations, the gap remains helpful, but only as part of a broader toxicology evaluation.
The best use of the anion gap is as a diagnostic clue. It may uncover hidden acids, supports the recognition of mixed acid-base disorders, and prompts further evaluation. But it is not definitive. Careful clinical judgment is still essential, especially when the presentation raises concern for systemic toxicity but the numbers are not easy to interpret.
Frequently Asked Questions About Anion Gap and Salicylate Toxicity
How does anion gap calculator help in salicylate poisoning?
An anion gap calculator assists by rapidly showing whether there is an unclear increase in unmeasured acids, which can support suspicion for salicylate poisoning. It is especially helpful when used with serum chemistry, an arterial blood gas, and the clinical picture. In toxicology, it serves as an first diagnostic clue rather than a final answer.
Can salicylate poisoning occur with a normal anion gap?
Yes. A normal anion gap result can be seen in early poisoning, in mixed acid-base disorder, or when reduced albumin masks the abnormality. For this reason a normal finding should not create a false sense of security. If the medical history or symptoms suggest aspirin poisoning, further testing and medical correlation are still needed.
Why do patients with aspirin toxicity often have both respiratory alkalosis and metabolic acidosis?
Aspirin stimulate breathing, leading to respiratory alkalosis, while also impairing metabolism and producing organic acids, which causes metabolic acidosis. This pattern creates a mixed acid-base disorder that can be seen on the arterial blood gas and in the anion gap. The pattern is a hallmark of toxicology evaluation for salicylate exposure.
Should the anion gap be corrected for albumin in suspected poisoning?
Absolutely, especially if albumin is low. Albumin contributes to the unmeasured anions in blood, so hypoalbuminemia can hide a meaningful gap elevation. A corrected anion gap improves acid-base interpretation and reduces the chance of missing toxic ingestion.
What labs should be checked after finding a high anion gap in suspected salicylate toxicity?
Check a salicylate level, complete electrolytes, bicarbonate, kidney function, lactate, and an arterial blood gas. Follow-up testing may be needed because the pattern can change over time. If the case is concerning, contact poison control and continue the poisoning workup with careful clinical judgment.