Understanding the Anion Gap?
The anion gap is a computed value that assists clinicians determine the gap between commonly measured electrolytes in the blood. It is most often used as a diagnostic clue in metabolic acidosis, where it can help identify whether excess acids or other unmeasured anions are present.
At its core, the anion gap reflects the relationship between sodium, chloride, and bicarbonate. Because the body maintains electrical neutrality, the measured positive and negative charges should balance. When they do not, the gap can point toward an electrolyte imbalance or another metabolic abnormality that needs further assessment.
The anion gap is not a direct test. Instead, it is a derived estimate that supports acid-base balance evaluation and broader acid-base disorders evaluations. In practice, it is best viewed as a initial and interpretation tool rather than a independent diagnosis.
How the Anion Gap Calculator Functions
An anion gap calculator relies on a simple formula built on routine test values. A common approach is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some calculators also include potassium, while many clinicians exclude it because the value typically adds little to everyday interpretation. If potassium is included, the formula becomes:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
This process uses serum electrolytes from a serum chemistry panel or more comprehensive metabolic panel. The result can indicate whether there may be a accumulation of acid load or another shift in ion levels. Since bicarbonate is often reduced in acidosis, the calculator is particularly helpful in the assessment of serum bicarbonate values and related acid-base interpretation.
The calculator is a practical diagnostic tool because it transforms everyday laboratory values into a more useful assessment of acid-base status. Used correctly, it aids clinical decision making by highlighting patterns that need further attention.
Standard Anion Gap vs High Anion Gap Metabolic Acidosis
Understanding the difference between standard anion gap metabolic acidosis and elevated anion gap metabolic acidosis is crucial for correct interpretation. Each are forms of metabolic acidosis, but they stem from separate mechanisms.
In standard anion gap metabolic acidosis, the bicarbonate drops, but the loss is usually matched by a increase in chloride. This pattern is often called chloride-rich acidosis. The anion gap stays within the expected range because the decrease in one measured ion is offset by an increase in another.
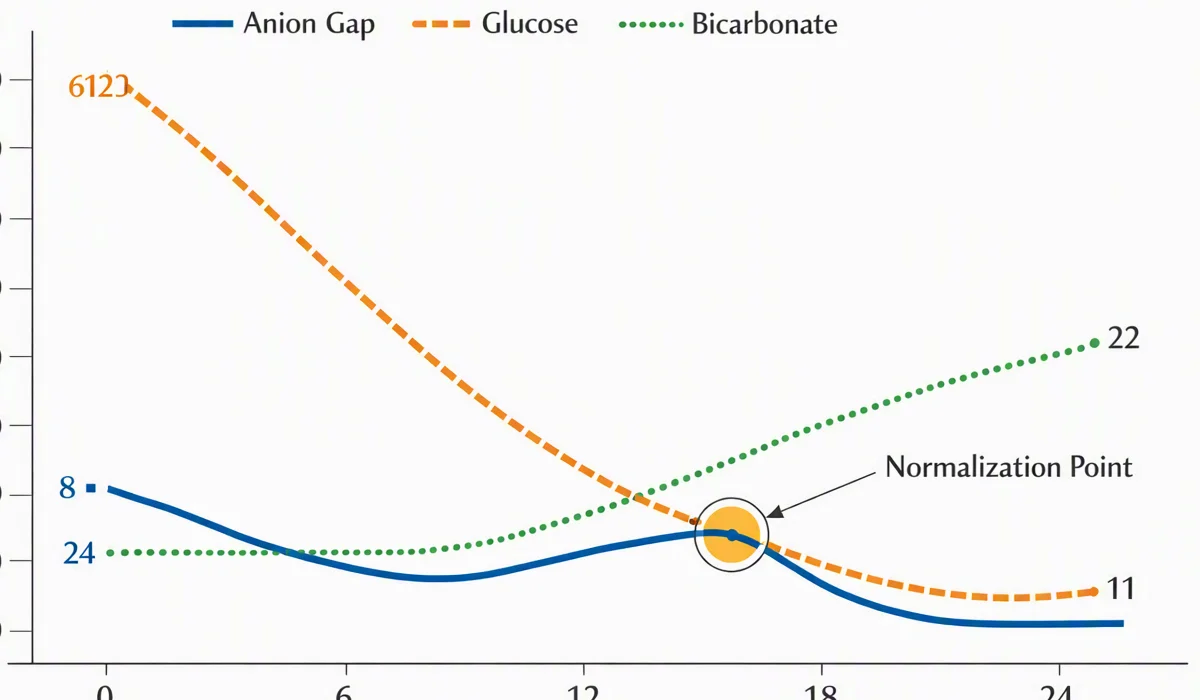
In high anion gap metabolic acidosis, bicarbonate decreases and there are additional unmeasured acids in the blood. These acids leave behind their anions, which widens the gap. This pattern indicates a higher accumulation of unmeasured anions and typically requires a search for causes such as lactic acidosis, ketoacidosis, renal dysfunction, or toxic exposures.
From a clinical standpoint, the distinction matters because it focuses the https://anion-gap-calculation.com/acid-base-disorders/nagma.html differential diagnosis. A normal anion gap pattern suggests toward causes of bicarbonate loss, while a elevated anion gap pattern suggests toward acid production, acid retention, or impaired clearance.
Interpreting the Result
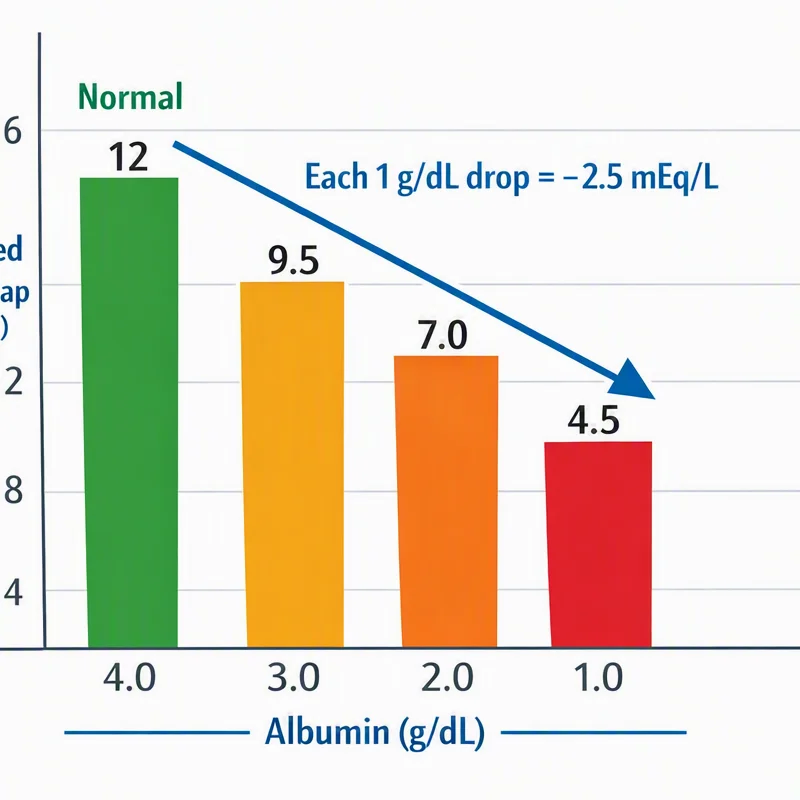
Evaluating an anion gap result takes more than checking the number to a reference range. The first step is to determine whether albumin is low, because albumin is a major unmeasured anion and greatly influences the value. When albumin is reduced, the gap may look falsely normal even when clinically important acidosis is present.
At this point the corrected anion gap becomes important. The correction adjusts the measured result upward when albumin is low, improving diagnostic accuracy. This process is often called albumin adjustment or anion gap correction, and it can reveal hidden high-gap acidosis that would otherwise be missed.
The delta gap is another useful concept. It compares the change in anion gap to the change in bicarbonate and can uncover mixed acid-base disorders. For example, a patient may have high anion gap acidosis plus a concurrent metabolic alkalosis, which can make the bicarbonate appear less reduced than expected.
Proper interpretation always integrates the calculator result with the patient’s clinical assessment. Symptoms, history, medications, renal function, and other laboratory findings matter. A single number rarely gives the full picture.
Practical interpretation questions include:
- Is the the anion gap truly elevated after albumin correction? Is the bicarbonate change fit the expected pattern? Are there signs of mixed acid-base disorders? Does the clinical context suggest lactate elevation, ketones, renal impairment, or toxins?
Typical Causes of Elevated Anion Gap
An elevated anion gap usually means that additional acids are present or that acid clearance is impaired. The most common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and certain toxins.
Lactic acidosis happens when lactate accumulates, often due to tissue hypoperfusion, severe illness, seizures, or other situations of increased anaerobic metabolism. Because lactate is an unmeasured anion, the anion gap rises as bicarbonate falls.
Ketoacidosis may occur with diabetes, prolonged fasting, or alcohol-related metabolic states. Ketone bodies serve as unmeasured acids, producing a high anion gap metabolic acidosis that often requires urgent treatment.
Renal failure and uremia reduce the body’s ability to excrete acid and preserve normal acid-base homeostasis. As retained acids accumulate, the anion gap can rise markedly.
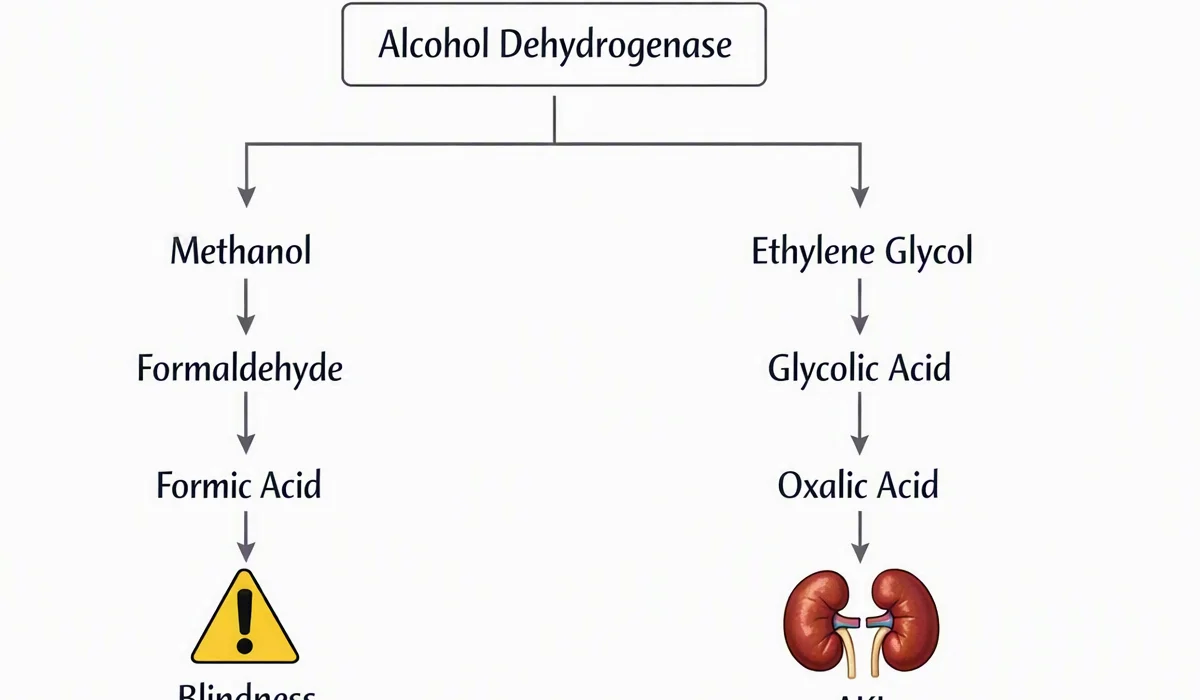
Toxins are another important category. Certain ingestions can cause profound acid-base disruption and may present with an increased gap. In these cases, the calculator is simply one part of the evaluation, not the entire diagnosis.
There may be other causes, but these major categories make up many clinically important cases of elevated anion gap metabolic acidosis. Identifying the pattern helps direct focused testing and prompt treatment.
Medical Context and Limitations
This anion gap is helpful, but it has important limitations. The result must always be interpreted alongside the blood gas, serum chemistry panel, and the wider clinical situation. The calculator cannot take the place of bedside judgment or the full evaluation of acid-base disorders.
A key limitation is inconsistency in the laboratory reference range from one lab to another. Multiple analyzers, different measurement methods, and different addition or exclusion of potassium can all affect the value. That means a “normal” number in one setting may not match exactly in another setting.
Another limitation is the effect of albumin. Without correction, the anion gap may downplay clinically meaningful abnormalities. Also, the gap does not determine the exact acid responsible; it only implies that unmeasured anions may be present.
A blood gas helps establish acid-base status by showing pH and carbon dioxide, while the serum chemistry panel delivers the electrolyte data needed for calculation. In combination, these results strengthen stronger diagnostic interpretation. The best use of the calculator is as part of a structured patient evaluation, not as a replacement for it.
Important pitfalls include:
- Believing a normal gap excludes all clinically significant acidosis Missing low albumin when evaluating the result Not remembering to compare the gap with bicarbonate using the delta gap Relying on the calculator without considering the blood gas and clinical context
Step-by-Step Sample Calculations
An illustrative calculation demonstrates how the formula works in real-world use. Review these electrolyte values:
- Sodium: 140 Chloride: 102 Bicarbonate: 18
With the formula, the anion gap is:
140 − (102 + 18) = 20
This value indicates a increased anion gap metabolic acidosis, if the local reference range is lower than 20. The next step would be to evaluate the clinical picture for causes such as lactic acidosis, ketoacidosis, renal failure, or toxins.
Next add albumin to the picture. If albumin is low, the measured gap may mask the problem. A corrected anion gap can be calculated using albumin adjustment to improve the estimate of the true burden of unmeasured anions.
For a second case, imagine a patient with the following values:
- Sodium: 138 Chloride: 112 Bicarbonate: 18
The calculation is:
138 − (112 + 18) = 8
This may fit a normal anion gap metabolic acidosis pattern, especially if bicarbonate is low and chloride is relatively high. In that setting, the interpretation may point more toward bicarbonate loss rather than excess unmeasured acids.
In a more advanced scenario, the corrected bicarbonate and the delta gap can be used together. If the anion gap is elevated but bicarbonate is not as low as expected, a mixed disorder may be present. That kind of interpretation is especially valuable when acid-base balance is complex and multiple processes overlap.
These illustrations show why calculator use is only the first step. The final interpretation depends on whether the numbers match the clinical story and whether additional testing supports the same conclusion.
FAQ About the Anion Gap Calculator
What does a Anion Gap Calculator assess?
An Anion Gap Calculator calculates the variation between key measured electrolytes, usually sodium, chloride, and bicarbonate. The result suggests whether there are excess unmeasured anions in the blood and helps evaluate metabolic acidosis and other acid-base disorders.
What is considered a normal anion gap range?
The normal anion gap range depends on the laboratory reference range used by the testing method. Because labs differ, it is best to read the result using the reference range provided with the patient’s serum chemistry panel and the overall clinical context.
Why is it corrected the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anion. When albumin is low, the measured anion gap may appear falsely normal. Correcting for albumin improves diagnostic accuracy and helps reveal hidden metabolic acidosis.
What causes a high anion gap metabolic acidosis?
Common causes include lactic acidosis, ketoacidosis, renal failure, uremia, and toxins. These conditions elevate unmeasured anions or reduce acid clearance, which raises the anion gap and lowers bicarbonate.
How does the delta gap used in anion gap interpretation?
The delta gap compares the change in anion gap with the change in bicarbonate. It helps identify mixed acid-base disorders, such as high anion gap metabolic acidosis combined with metabolic alkalosis or a normal anion gap process. This helps make interpretation more precise during patient evaluation.